Epidemiology Incidence highest incidence in patients with acetabular dysplasia Demographics seen in all age groups patients commonly active females Anatomic location anterosuperior labrum most common location Etiology Pathophysiology femoroacetabular impingement hip dysplasia floppy labrum more susceptible to tearing trauma hip dislocations/subluxations are a common cause capsular laxity increased translational forces across labrum due to joint hypermobility joint degeneration causes acetabular edge loading Anatomy Structure horse-shoe shaped structure continuous with transverse acetabular ligament 2 parts articular capsular Vascularity capsule and synovium at acetabular margin only peripheral 1/3rd of the labrum is vascularized Innervation highly innervated with mechanoreceptors and nocioreceptors branch of nerve to the quadratus femoris obturator nerve Presentation Symptoms mechanical hip pain and snapping may have vague groin pain may be associated with a sensation of locking Physical exam provocative tests anterior labral tear posterior labral tear Imaging Radiographs useful to exclude other types of hip pathology may show hip dysplasia arthritis acetabular cysts imaging study of choice 92% sensitive for detecting labral tears may be combined with intra-articular injections of lidocaine and steroid for diagnostic and therapeutic purposes Treatment Nonoperative rest, NSAIDS, physical therapy, steroid injections indications outcomes arthroscopic labral debridement indications technique outcomes arthroscopic labral repair indications outcomes labral reconstruction indications outcomes Create a free account or log in to see the cards.

Favorable 98% Mixed 2% Unfavorable overall 0% Most reported benefits Benefits users selected when logging a favorable or mixed check-in
The goal is always to maximize efficacy while minimizing invasiveness and side effects
Nutritional optimization instead of supplementation Focusing on b12-rich foods may provide adequate amounts for many patients
KLOW is the more relevant blend for reactive or rosacea-prone skin
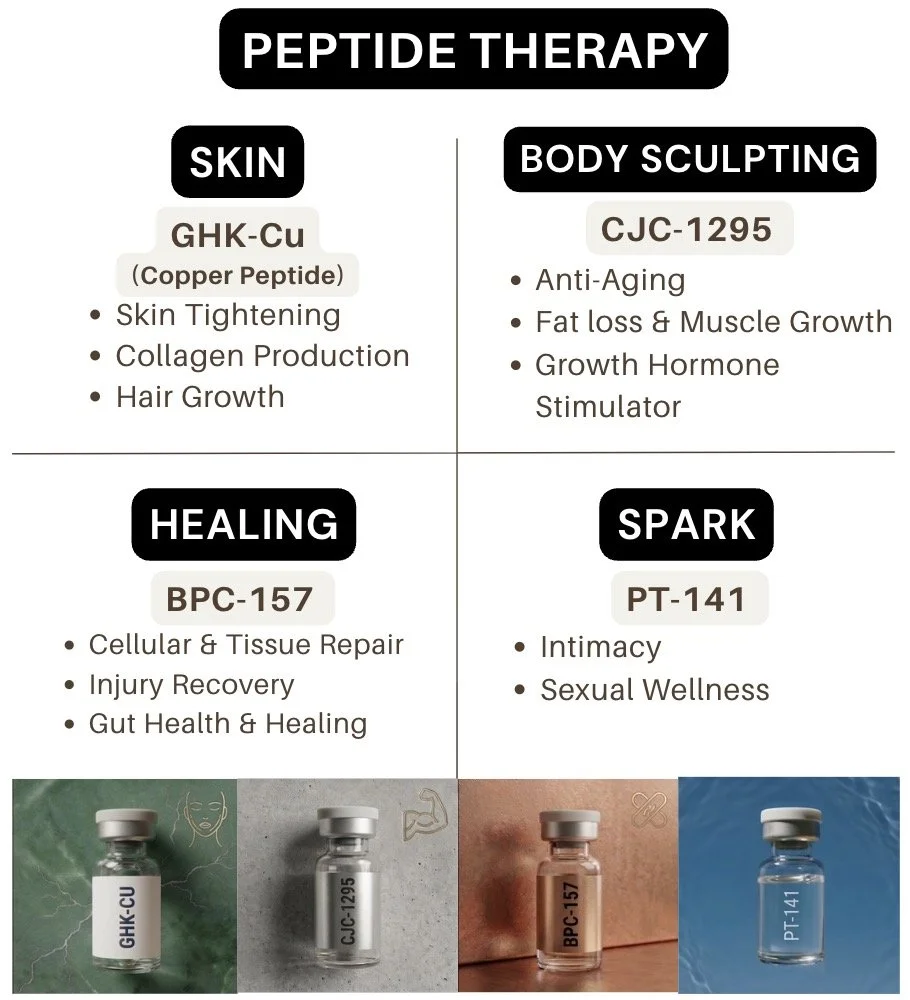
Based on clinical observation, self-experimentation, and available research, heres what Ive consistently seen: A single dose of BPC-157 (typically 250-500 mcg) produces measurable biological effects for 24-48 hours