TB-500 has also been suggested to support cystic fibrosis due to its potential impact on sputum cohesivity, which has been observed to be decreased following TB-500 exposure
The standard research protocol is 300 mcg per day, subcutaneous, administered in a fasted state, typically in the morning before food or exercise
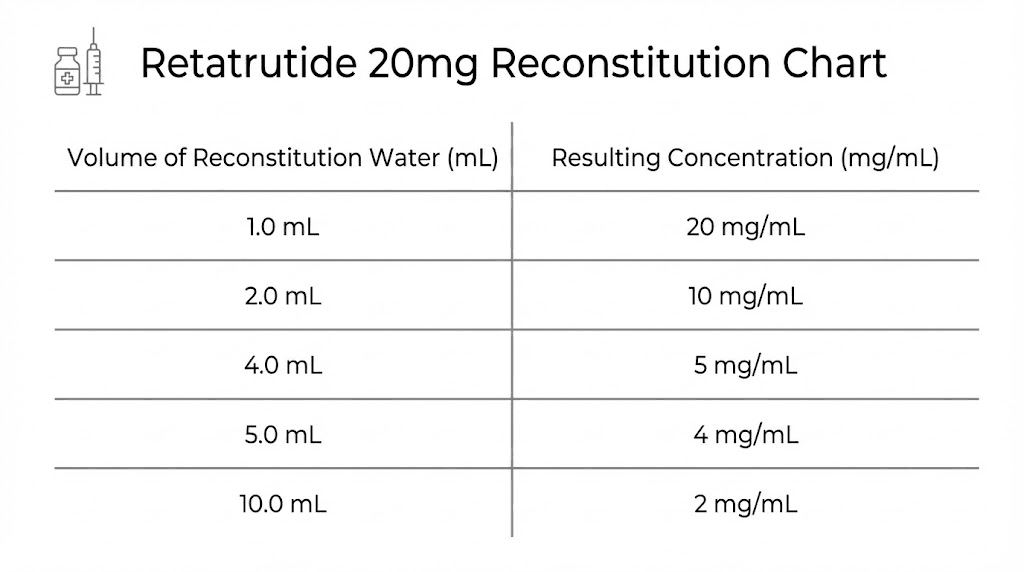
Always remember to remove air bubbles from the pin by flicking it gently, pin side up, and pushing bubbles out
In principle, synergy is plausible in a few situations: Complementary pathways (e.g., appetite control + strength training adherence) Non-overlapping side-effect profiles Clear outcome tracking (so you can actually attribute effects) Where it tends to fall apart: Redundancy (two agents trying to push the same pathway) Hormonal axis pressure (especially GH/IGF-1 axis stacking) Long timelines with weak evidence (people run stacks for months because its peptides, not because outcomes justify it) For the rest of this article, Ill treat each stack as a clinical hypothesis and ask a simple question: If this were my patient, what would I be confident saying based on human evidenceand what would I label unknown? The 7 stacks people search for most (and what the evidence really supports) Quick comparison table Now, lets go stack by stack
Univariate comparisons between patient groups were analyzed using the Students t -test or the MannWhitneys U-test, as appropriate
2.B12 is combined with a protein manufactured by your body called Intrinsic Factor (IF) and gets absorbed by your liver